
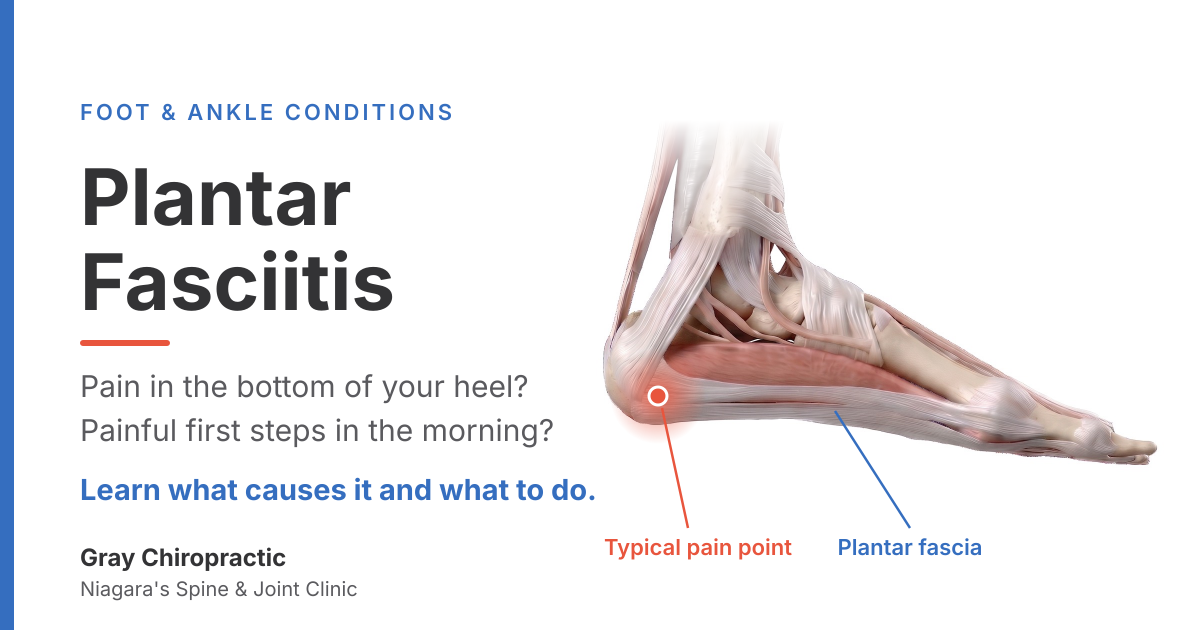
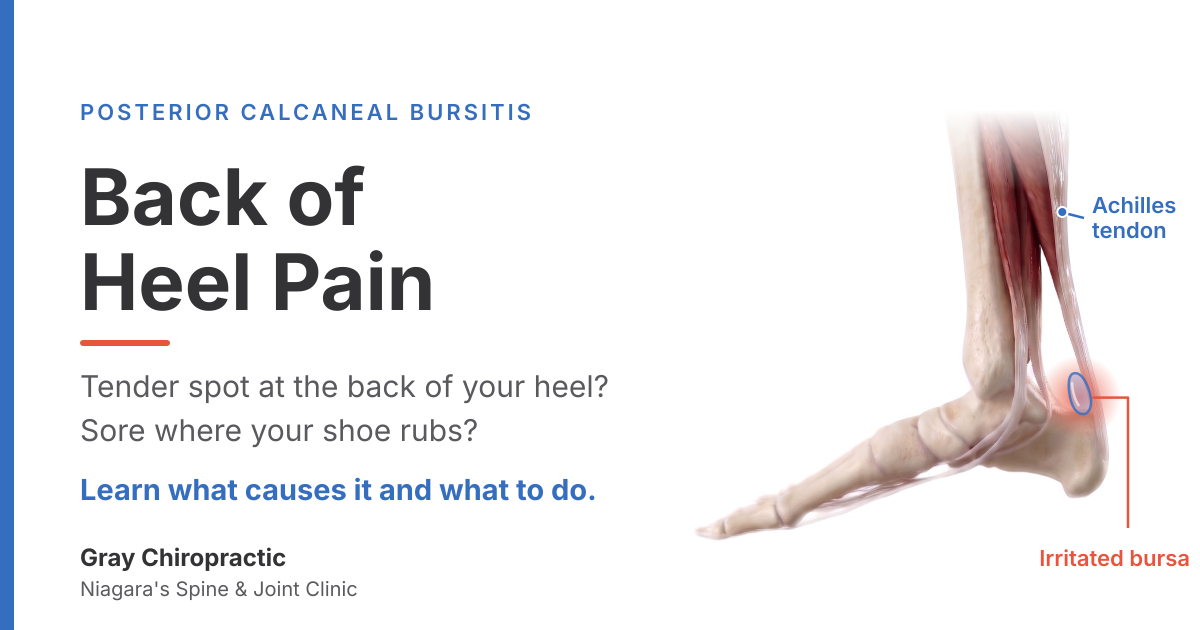
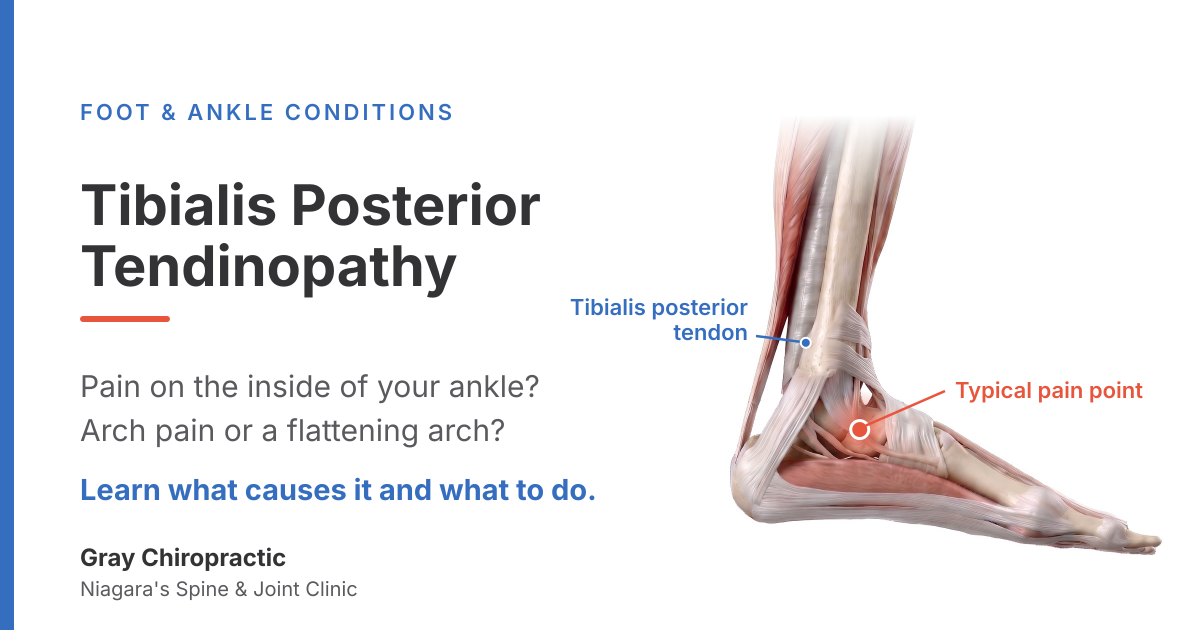
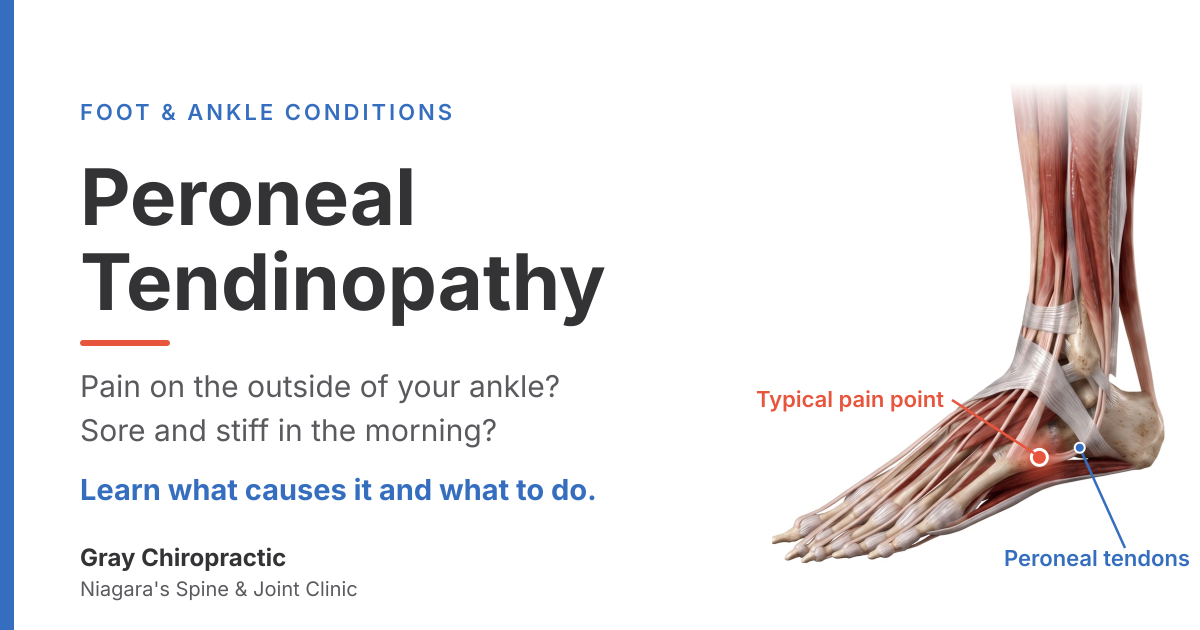
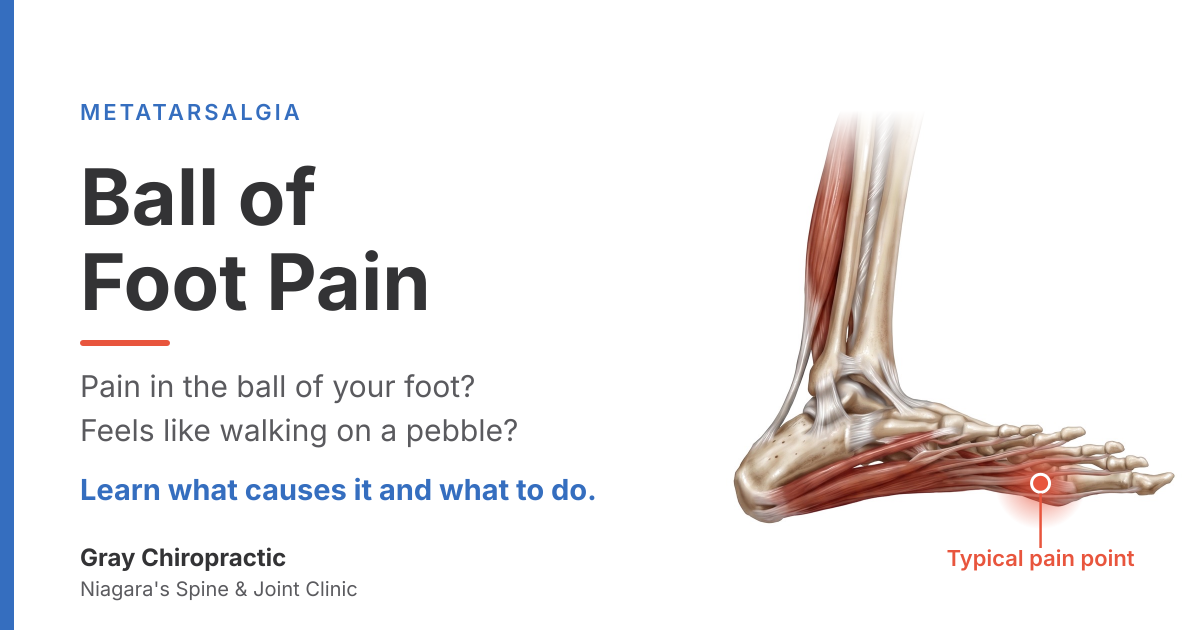
Heel pain with your first steps in the morning? An ache on the inside or outside of your ankle? A sore spot at the back of your heel, or a feeling like you’re walking on a pebble?
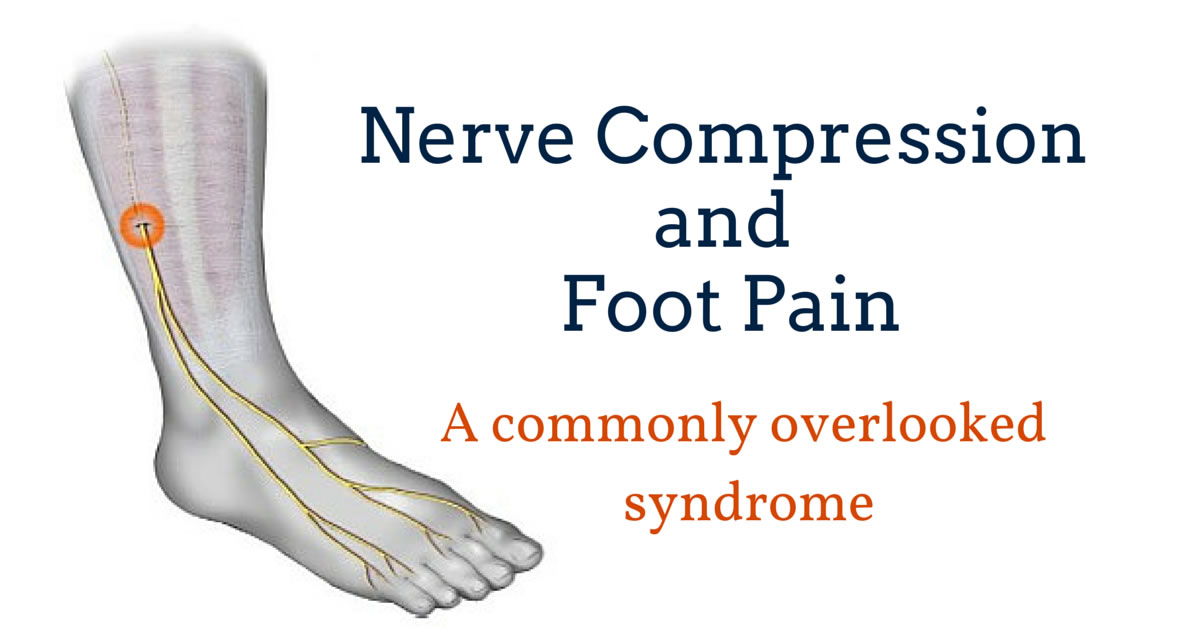
If that sounds like you, you’re in the right place. Even though we’re chiropractors, foot pain is one of the most common problems we see and treat. In fact we treat a wide range of foot and ankle conditions such as plantar fasciitis, posterior calcaneal bursitis, achilles tendinopathy, tibialis posterior tendinopathy, peroneal tendinopathy, metatarsalgia, and nerve entrapments that may be affecting the foot.
The important thing to remember is that all of these conditions fall into the category of Cumulative Trauma Disorders (CTDs). Which means they don’t occur after a specific trauma or single event. With CTDs damage and injury occurs slowly over time. Which is why it just seems to show up one day, often after something routine like a long walk or a shift on your feet.
And as we’ll see below, that makes a big difference in how this type of foot pain needs to be treated.
Learn more about specific foot conditions:
Browse Our Foot Pain Articles

Swipe or scroll sideways to see more →
Our Approach To Foot Pain (Why Foot Pain Is Really Two Problems)
The key to resolving CTDs is understanding that there are actually two problems that need to be addressed. First, we have to address the damage itself. Make no mistake, even though these injuries develop slowly over time, they’re still injuries. So whether a degenerated tendon, damaged plantar fascia, or inflamed nerve, these injured tissues need to heal.
While the exact treatment will depend on the specific condition, there are several in-office treatments that can have a powerful impact on tissue healing.
In the clinic. Our main hands-on treatments are Active Release Technique (ART) and Functional Range Release (FR). The foot has many small muscles stacked in layers, and they need to stretch and slide against each other to work properly. These techniques let us find and release individual restrictions between layers, which you can’t do on your own. Shockwave treatment is another powerful tool. This technology uses high-pressured sound waves that are able to stimulate damaged tissue to heal and regenerate through a process known as mechanotransduction.
At home. Every patient also gets stretches and exercises that help rehabilitate the injured tissue. But this is not going to be a generic set of exercises, or a one-size-fits-all prescription. These home exercises — what exercises, how many and how often, and intensity — need to be specific to each individual patient. Two people with the same diagnosis often need different exercises, which is why generic routines from YouTube or TikTok so often fall short.
But that’s not enough. We also need to address why the condition developed in the first place.
But Why Did This Happen?
As important as tissue healing and rehabilitation is, it alone is rarely enough. It doesn’t address why the condition developed in the first place. If we don’t understand and correct the cause, it’s going to be very hard to get the problem to fully resolve.
Here we must understand that non-traumatic foot pain doesn’t start as an injury. It starts with subtle muscle weakness, limited flexibility, or muscle imbalances around the foot and ankle. When this happens, your foot doesn’t just stop working — you can still walk, run, and go up and down stairs. But it isn’t working normally anymore, because it’s compensating for those imbalances.
At first, these subtle problems go unnoticed. But those compensations have a way of catching up with you. They create abnormal stress patterns and microtrauma in and around the foot, and as that pattern continues, small-scale stress and damage can build into a larger-scale injury and real pain.
This is how most cases of non-traumatic foot pain develop. Here are some common examples:
- A stiff ankle can push the foot to roll inward (hyperpronation). That overloads the plantar fascia or the tibialis posterior tendon. An orthotic alone rarely fixes this, because the ankle itself needs to move better.
- A stiff big toe changes how you push off. That shifts stress to the outer ankle, the inner ankle and the ball of the foot.
- Weak muscles in the foot itself can’t properly support the joints. This weakness can lead to joint strain and instability.
The challenge is that these underlying mechanical problems are different for every patient — there’s no single movement flaw that causes any one specific condition. Take plantar fasciitis, for example. In some patients, hyperpronation is a major factor. In others, it’s the opposite — an excessively tight, stiff foot that doesn’t pronate enough. And in some cases, a tight calf and ankle are the real problem.
All of these patients share the same diagnosis, but each case has its own unique contributing deficits that need to be addressed. Once again, we see why a generic set of foot exercises pulled from YouTube or TikTok so often falls short. Stretches and exercises need to be customized to the individual patient.
Why a Proper Assessment Matters
This is why every patient goes through a full assessment in our clinic — not just to identify what hurts, but to uncover every mobility limitation, imbalance, and weakness that needs to be addressed. That assessment is what allows us to be so effective in treating foot pain. Once we understand the strength and mobility limitations related to each specific patient, we are able to work that into the treatment plan.
Problem 1: The irritated muscle, tendon or fascia that is causing the pain. It needs to heal and be rehabilitated.
Problem 2: The strength, flexibility and mobility problems that overloaded it in the first place.
Treat only the pain and the cause keeps doing damage. Lasting relief means treating both.
Watch: How We Treat Foot Pain
Before You Book
If this approach sounds like a good fit for a foot condition you’re dealing with, my staff would be glad to help you book. Before you call, here are a few things worth knowing. First, this isn’t a quick fix. Healing tissue and rebuilding strength, flexibility, and muscle balance takes real time and effort — both on my part and yours.
For longstanding symptoms, typical treatment plans run about 6-8 weeks. In-clinic visits are usually twice a week early on, tapering off as you progress. Home exercises typically take about 20–30 minutes a day.
If your schedule doesn’t currently allow for that kind of commitment, it’s worth thinking through before starting this approach to care.
What to expect: This isn’t a quick fix.
- Most plans for longstanding pain run about 6-8 weeks.
- Visits are usually twice a week at first, then less often.
- Home exercises take about 20-30 minutes a day.
If your schedule can’t fit that right now, it’s worth thinking over before you start.
Ready to Get Started?
Book your appointment here or call us at (905) 685-7227.